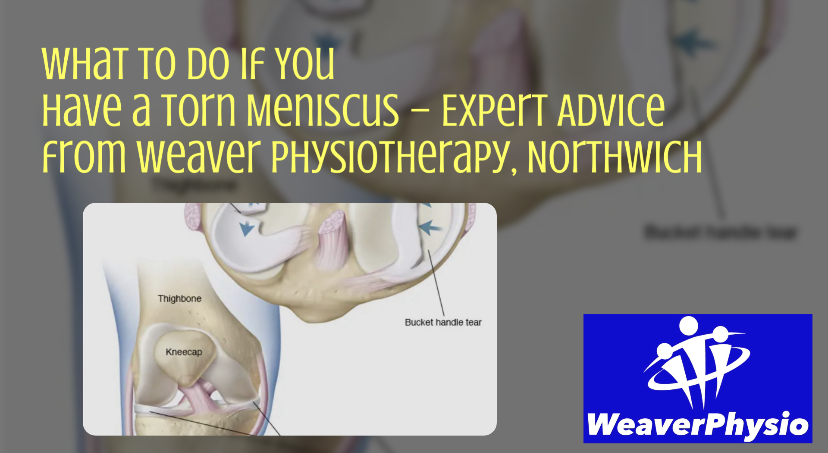
What To Do If You Have a Torn Meniscus

October 7, 2025

 Expert Advice from Weaver Physiotherapy, Northwich
A torn meniscus is one of the most common knee injuries seen by physiotherapists, especially among runners, footballers, and active individuals. Whether it happens during sport or through gradual wear and tear, a meniscus tear can be painful, limit movement, and affect your ability to walk, squat, or run comfortably.


At Weaver Physiotherapy & Sports Injury Clinic in Northwich, Cheshire, our Chartered Physiotherapists regularly treat patients with meniscus injuries — helping them recover strength, mobility, and confidence without unnecessary surgery.


In this blog, we’ll explain everything you need to know about a torn meniscus, including:

    •    What the meniscus does

    •    How meniscus tears happen

    •    Common symptoms and diagnosis

    •    What to do immediately after injury

    •    How physiotherapy helps recovery

    •    When surgery may be needed

    •    The best exercises for rehabilitation

    •    How to prevent future knee injuries


🦵 What Is the Meniscus?


The meniscus is a C-shaped pad of cartilage that acts as a shock absorber between your thigh bone (femur) and shin bone (tibia). Each knee has two menisci – the medial meniscus (inside) and the lateral meniscus (outside).


These structures:

    •    Distribute weight across the knee joint

    •    Improve joint stability

    •    Help with smooth, controlled movement

    •    Protect the articular cartilage from excessive wear


When the meniscus is torn, these functions are compromised, leading to pain, swelling, and difficulty bearing weight.


⚡ How Does a Meniscus Tear Happen?


Meniscus tears occur in two main ways: acute injuries and degenerative changes.


1️⃣ Acute Meniscus Tears


These usually occur suddenly, often during sport or twisting movements.

Common causes include:

    •    Twisting the knee while the foot is planted

    •    Sudden changes in direction (common in football, tennis, rugby)

    •    Deep squatting or heavy lifting

    •    Direct impact or trauma to the knee


2️⃣ Degenerative Meniscus Tears


These develop gradually with age or repetitive stress. The cartilage becomes thinner and less resilient, meaning even a small twist or awkward movement can cause a tear. This type is common in people over 40.


🚨 Symptoms of a Torn Meniscus


The symptoms vary depending on the severity and location of the tear, but typical signs include:

    •    Pain along the joint line (often on the inner or outer side of the knee)

    •    Swelling and stiffness, which may appear a few hours after the injury

    •    Locking or catching sensation in the knee

    •    Difficulty straightening or bending the knee fully

    •    Clicking or popping sounds when moving

    •    Feeling of instability or the knee “giving way”


If you notice these symptoms — especially following a twist, squat, or sports incident — it’s important to get assessed by a qualified physiotherapist.


🧠 Diagnosis: How Is a Meniscus Tear Confirmed?


At Weaver Physiotherapy, your clinician will carry out a detailed clinical assessment that includes:

    •    Medical history & mechanism of injury – how and when it happened

    •    Observation & palpation – checking swelling, alignment, and tenderness

    •    Functional tests – such as the McMurray or Apley’s test to reproduce symptoms

    •    Strength & stability testing – evaluating surrounding muscles and ligaments


If a significant tear or other knee injury is suspected, your physiotherapist may recommend imaging such as:

    •    MRI scan – the gold standard for confirming meniscus tears

    •    X-ray – to rule out fractures or osteoarthritis


🧊 What To Do Immediately After a Meniscus Injury


If you suspect a meniscus tear, it’s crucial to act quickly to minimise swelling and further damage.


Follow the POLICE principle:


P – Protect: Avoid activities that cause pain or twisting. Use crutches if necessary.

O – Optimal Loading: Gentle movement within a pain-free range keeps the joint mobile.

L – Ice: Apply ice packs for 15–20 minutes, 3–4 times a day to reduce swelling.

I – Compression: Use an elastic knee sleeve or bandage to limit swelling.

C – Elevation: Rest with your leg raised above heart level where possible.


Avoid “HARM” in the first 48 hours:

    •    H – Heat

    •    A – Alcohol

    •    R – Running

    •    M – Massage


These can increase bleeding and swelling in the joint.


🩺 How Physiotherapy Helps a Torn Meniscus


Physiotherapy is a key part of recovery, whether your tear is treated conservatively or after surgery. At Weaver Physio, we create personalised rehabilitation programmes to restore function and reduce pain.


Our approach includes:

    •    Hands-on treatment to ease stiffness and improve joint mobility

    •    Progressive strengthening exercises for quadriceps, hamstrings, and glutes

    •    Balance and proprioception training to improve stability

    •    Shockwave Therapy (for chronic pain or associated tendon issues)

    •    Acupuncture to reduce pain and swelling

    •    Rehabilitation planning for safe return to sport or daily activity


🕒 Recovery Without Surgery


Many people recover well without needing surgery, particularly for:

    •    Small or partial tears

    •    Degenerative (age-related) tears

    •    Stable knees without locking


Conservative treatment focuses on reducing swelling, regaining range of motion, and gradually rebuilding strength.


A typical non-surgical recovery timeline may look like:

    •    0–2 weeks: Reduce swelling and pain; gentle range of motion

    •    2–6 weeks: Begin strengthening and controlled weight-bearing

    •    6–12 weeks: Restore function, stability, and gradual return to sport


⚙️ When Is Surgery Needed?


Not all meniscus tears heal on their own. Surgical intervention may be considered when:

    •    The knee locks or catches repeatedly

    •    Pain persists after 6–12 weeks of physiotherapy

    •    The tear is large, displaced, or in the vascular (outer) zone

    •    The patient is young and active with a traumatic injury


Common surgical options include:

    •    Arthroscopic Meniscectomy: Removal of the damaged portion of the meniscus

    •    Meniscus Repair: Stitching the torn section together (used for tears with good blood supply)

    •    Meniscus Replacement (Allograft): Rarely, a donor graft may be used for extensive damage


Following surgery, physiotherapy remains essential to restore strength, motion, and confidence.


🏋️‍♀️ Best Exercises for Meniscus Rehabilitation


(Always consult a physiotherapist before starting any new exercise programme.)


1️⃣ Quadriceps Setting

    •    Sit with your leg straight.

    •    Tighten your thigh muscles and press the back of your knee into the floor.

    •    Hold for 5 seconds, then relax.

    •    Repeat 10–15 times.


2️⃣ Heel Slides

    •    Lie on your back with legs straight.

    •    Gently slide your heel towards your buttocks, bending the knee as far as pain allows.

    •    Slowly return to start.

    •    Repeat 10–15 times.


3️⃣ Straight Leg Raises

    •    Lie flat on your back.

    •    Keep one leg straight and the other bent.

    •    Lift the straight leg to about 30–40cm.

    •    Hold for 3–5 seconds and lower slowly.


4️⃣ Mini Squats

    •    Stand with feet shoulder-width apart.

    •    Gently bend knees to 30°, keeping heels on the floor.

    •    Hold for 2 seconds, then return upright.


5️⃣ Step-Ups

    •    Step onto a low platform or step, leading with the injured leg.

    •    Step back down slowly.

    •    Repeat 10–15 times.


These exercises help maintain muscle activation and support joint stability, essential for long-term knee health.


🔄 Returning to Sport After a Meniscus Tear


Returning to sport depends on the type of tear, treatment route, and rehabilitation progress.


Before returning to sport, you should:

    •    Have full range of motion

    •    Achieve equal strength in both legs

    •    Perform sport-specific movements (e.g. running, cutting, jumping) pain-free


At Weaver Physio, we use progressive sport-specific rehabilitation and video gait analysis to assess biomechanics, ensuring you return to training safely and reduce the risk of re-injury.


💬 Realistic Recovery Timeframes


Recovery time varies widely:

    •    Minor tear (no surgery): 6–8 weeks

    •    Surgical repair: 3–6 months

    •    Partial meniscectomy: 4–8 weeks


Your physiotherapist will monitor your progress and adjust your rehabilitation accordingly.


🧩 Preventing Future Meniscus Injuries


Once healed, maintaining strong, balanced knees is crucial to prevent recurrence.


Key prevention strategies:

    1.    Strengthen supporting muscles – focus on quads, hamstrings, glutes, and calves.

    2.    Improve hip and ankle mobility – helps reduce rotational stress on the knee.

    3.    Warm up properly – include dynamic stretches before exercise.

    4.    Train balance and proprioception – use wobble boards or single-leg exercises.

    5.    Wear supportive footwear – especially for running or high-impact sport.

    6.    Avoid deep twisting or pivoting movements if your knee feels unstable.


💡 Why Choose Weaver Physiotherapy for Meniscus Injury Treatment?


At Weaver Physiotherapy & Sports Injury Clinic, we combine decades of clinical experience with cutting-edge rehabilitation techniques.


Our physiotherapists specialise in knee injuries, working with both athletes and non-athletes across Northwich, Knutsford, Winsford, Middlewich, Frodsham, and throughout Cheshire.


What sets Weaver Physio apart:


✔️ 70+ years of combined clinical experience

✔️ Expert diagnosis and personalised rehabilitation plans

✔️ Advanced treatments including Shockwave Therapy, Acupuncture, and Gait Analysis

✔️ Evidence-based, hands-on physiotherapy

✔️ Trusted by local runners, footballers, and gym-goers

✔️ Focus on long-term recovery and performance


Whether you’re recovering from a meniscus tear, knee surgery, or chronic knee pain, we’ll help you move better, recover faster, and stay pain-free.


📞 Get Expert Help Today


If you suspect you have a torn meniscus or ongoing knee pain, don’t wait for it to worsen. Early diagnosis and physiotherapy make a huge difference in recovery and preventing long-term complications.


📍 Weaver Physiotherapy & Sports Injury Clinic

Northwich, Cheshire

🌐 https://www.weaverphysio.com

📞 Call 01606 227484 to book your appointment


By M NORMAN • October 8, 2026
A Practical Guide for Endurance Runners
October 7, 2026
Have you ever been told that your running style is “wrong” and immediately wondered whether you need to change it? Advice online can make normal differences in movement look like faults. While certain running habits may be worth exploring—particularly when pain keeps returning—there is no single perfect stride, cadence or foot strike for every runner. At Weaver Physiotherapy & Sports Injury Clinic, we take an individual approach to running technique. Your training history, symptoms, strength, mobility, goals and the way you respond to load all matter. For runners in Northwich, Middlewich, Winsford, Knutsford, Sandbach, Frodsham and Tarporley, our Runner’s MOT and running gait analysis⁠ provides clear, personalised feedback rather than generic rules. What are common running form mistakes? A “running form mistake” is often better described as a movement habit to investigate. A pattern may look unusual without being harmful, and a video alone cannot confirm that it is the cause of pain. Common concerns include: Overstriding – the foot appearing to land well ahead of the body. Upper-body tension – raised shoulders, clenched hands, a tight jaw or stiff arm swing. Forcing foot strike – deliberately trying to run on the forefoot or heel when it feels awkward. Slumped posture – losing trunk control as fatigue develops. Abrupt changes in technique – trying to alter cadence, posture and foot strike at the same time. These patterns can change with pace, hills, footwear, fatigue, confidence and training load. Research has found limited evidence that individual biomechanics alone predict running injury, which is why form should be considered alongside the wider picture rather than treated as a diagnosis. Is there one correct way to run? No. Effective running does not look identical from person to person. Your anatomy, strength, experience, speed, terrain and fatigue level all influence your stride. A single photograph or short clip captures only one moment. It cannot explain how you feel during a run, what your training has involved that week, or whether a movement pattern is actually contributing to symptoms. If you are comfortable, progressing well and free from persistent pain, you may not need to change your technique simply because it differs from someone else’s. The aim is not to chase a “perfect” running style. It is to understand your own movement and make sensible adjustments only when they are relevant to your goals or symptoms. How to assess your running form safely Start with one question. Perhaps your foot feels as though it reaches too far forwards, your shoulders tighten on longer runs, or you notice discomfort appearing as you fatigue. During an easy run at your usual pace, consider: Does your breathing feel relaxed? Are your shoulders, hands and jaw unnecessarily tense? Does your stride feel comfortable and natural? Does your movement alter later in the run? Is there recurring pain during, after or the following day? If you use video, record a brief clip from a safe, consistent position beside the route or on a treadmill. Never hold or watch a phone while running. Footage can be useful for observation, but it should prompt questions—not provide a self-diagnosis. How to change running technique without overdoing it Avoid making dramatic changes based on a social-media tip or a one-size-fits-all rule. A sudden change in cadence, posture or foot strike may feel unnatural and can make it difficult to work out what is helping. Instead: Choose one area to explore. Use one simple cue during an easy run. Keep the adjustment gentle and brief. Notice how it feels during the run and over the next 24–48 hours. Do not introduce several technique changes at once. For example, if you feel tense through the upper body, a helpful cue may be “soft shoulders and easy arms” rather than forcing a rigid posture. If you are concerned about stride length, focus on a light, comfortable rhythm rather than trying to land in a prescribed position. Training progression matters too. Increasing distance, pace, hills and frequency too quickly can overload tissues, regardless of how your running looks. NHS advice recommends building running gradually and listening to pain rather than pushing through it. Read the NHS guide to common running injuries ⁠. When should you seek individual running advice? Consider a running assessment if pain: Keeps returning or becomes more severe Changes the way you run Persists after reducing or adapting training Is associated with swelling, weakness, limping or a loss of confidence Leaves you unsure which changes, if any, are appropriate Sudden severe pain, inability to bear weight, major swelling, numbness, deformity or a suspected serious injury should be assessed urgently. NHS guidance on sprains and strains explains when to seek urgent help. What can running gait analysis help with? A running gait analysis does not promise to predict injury or reveal one universal correction. It can, however, provide a clearer view of movement patterns in the context of your symptoms, training and goals. At Weaver Physio, our Runner’s MOT (/runners-mot)⁠ combines slow-motion video gait analysis with strength, mobility and movement assessment. We look at factors such as: Running rhythm and lower-limb control Trunk, hip, knee and foot movement Strength, balance and mobility Previous injuries and current symptoms Training volume, recovery and running goals Your findings are then used to create practical, personalised recommendations. This may include a gradual gait cue, running-specific strength work, mobility exercises, load-management advice or a structured return-to-running plan. Our Chartered Physiotherapists and Sports Rehabilitators bring more than 70 years of combined clinical experience to help runners move with greater understanding and confidence. Build a stronger, more confident running stride Running form is not a test you have to pass. A movement pattern may be worth exploring, but it does not automatically mean that something is wrong. Pay attention to comfort, recurring symptoms and changes that develop with fatigue. Make adjustments gradually, progress training sensibly and seek individual support if pain continues. For runners across Northwich and Cheshire, Weaver Physio’s running gait analysis service (/runners-mot)⁠ offers professional, tailored guidance to help you run stronger and with more confidence. Frequently Asked Questions Is there one correct running form for everyone? No. There is no single ideal foot strike, cadence or posture that applies to every runner. Comfortable, efficient running can look different depending on the individual, their pace, experience and physical characteristics. Can changing my running form cause pain? It can. Sudden or uncomfortable changes may increase stress in unfamiliar areas. Make one gradual change at a time and reduce or stop if pain worsens. How can I tell if I overstride? Overstriding may appear as the foot landing well ahead of your body, but this does not automatically mean it is causing a problem. A short video can provide useful context, while a gait assessment can help interpret the pattern alongside your symptoms and training. When should I book a running gait analysis? Book an assessment if pain is recurring, your running style has changed, you are returning from injury, or you would like clearer guidance about your stride and training. Weaver Physio supports runners from Northwich, Middlewich, Winsford, Knutsford, Sandbach, Frodsham, Tarporley and across Cheshire.
September 23, 2026
Expert Joint Care
September 21, 2026
Persistent pain at the back of the heel can make simple things—walking the dog, climbing stairs, training for the Knutsford 10K or enjoying a run around Tatton Park—feel far more difficult than they should. At Weaver Physiotherapy & Sports Injury Clinic, we provide shockwave therapy ⁠ as part of a structured rehabilitation programme for people with persistent Achilles tendon pain. Our Northwich clinic is easily accessible from Knutsford and supports active adults, runners and sportspeople across Cheshire. The goal is not simply to settle symptoms for a few days. It is to understand why the tendon is painful, improve its capacity for load, and help you return to the activities that matter to you with greater confidence. Achilles Tendinitis or Achilles Tendinopathy? “Achilles tendonitis” is the term most people use when describing pain, stiffness or swelling around the tendon at the back of the ankle. However, when symptoms have persisted for several weeks or months, the more accurate clinical term is often Achilles tendinopathy. Tendinopathy is a complex condition associated with tendon pain, reduced function and lower tolerance to exercise or repeated loading. The tendon may become more sensitive and less able to cope with the demands being placed upon it. It is not always a straightforward inflammatory problem, which is why complete rest, stretching or massage alone may not create a lasting solution. A detailed review of tendinopathy research describes the changes that can occur within painful tendons and the importance of an individualised management approach. Common symptoms include: Pain or stiffness at the back of the heel, especially first thing in the morning Discomfort when walking uphill, climbing stairs or rising onto tiptoes Pain during or after running, football, tennis, gym training or long walks Thickening or tenderness in the tendon Symptoms that improve as you warm up, then return later At Weaver Physio, we assess whether your symptoms are likely to be related to mid-portion or insertional Achilles tendinopathy, and screen for other possible causes of heel and calf pain. If there is concern about a rupture, significant tear or another condition requiring medical investigation, we will advise on the appropriate next step. What Is Shockwave Therapy? Extracorporeal Shockwave Therapy—often shortened to ESWT or radial shockwave therapy—uses controlled acoustic pressure waves delivered through a handheld applicator. It is not an electric shock and does not involve injections or surgery. During treatment, gel is applied to the skin and the handpiece is positioned over the relevant area of the Achilles tendon. The sensation is commonly described as firm tapping or pulsing. Your clinician can adjust the treatment intensity to keep it manageable. Shockwave therapy may be considered for longer-standing tendon pain, particularly where a well-planned rehabilitation programme has not yet delivered the progress you need. It should always be used following a thorough assessment and alongside progressive exercise—not as a standalone “quick fix”. How Shockwave Therapy May Help Achilles Pain Shockwave therapy is thought to influence pain sensitivity and stimulate biological responses within the tendon and surrounding tissues. The practical aim is to create a window in which you can move more comfortably and build strength more effectively. For Achilles tendinopathy, a comprehensive treatment plan may help you to: Reduce pain that is limiting walking, work or sport Improve confidence with daily activity and exercise Progress calf-strength and tendon-loading exercises more successfully Address training errors, footwear issues and movement factors contributing to overload Build resilience for a return to running, sport or long-distance walking Outcomes vary between individuals. Some people notice a change in symptoms early in treatment, while tendon adaptation and improvements in load tolerance typically take longer. We will always discuss realistic expectations and measure your progress against your own goals. Your Shockwave Therapy Assessment Near Knutsford Your journey starts with a detailed physiotherapy assessment. We look beyond the painful spot to understand the full picture, including: Your symptom history and training or activity levels Previous injuries and treatment Calf strength, ankle mobility and balance Achilles tendon tenderness and loading tolerance Footwear, running surface and recent changes in training volume Hip, knee and foot control where relevant This allows us to confirm whether shockwave therapy is an appropriate option and develop a recovery plan tailored to you. Weaver Physio’s team also provides specialist physiotherapy and sports injury rehabilitation ⁠, so your treatment can be integrated with hands-on care, exercise rehabilitation and return-to-sport planning where needed. What Does a Typical Course Involve? A course of shockwave therapy commonly involves three to five sessions, often spaced about one week apart. The exact number and timing will depend on your presentation, response to treatment and rehabilitation goals. Each appointment is combined with guidance on tendon loading. This may include: Isometric calf exercises for pain management Progressive heel raises and heavy slow resistance work Soleus and gastrocnemius strengthening Balance, control and single-leg stability work A gradual return to running, hills, speed work or plyometric exercise Rather than avoiding all activity, we help you find an appropriate level of movement that keeps the tendon challenged without repeatedly exceeding its current capacity. Is Shockwave Therapy Right for You? Shockwave therapy may be suitable if you have persistent Achilles symptoms that have not settled with sensible activity modification and a targeted rehabilitation programme. It is particularly relevant for people who want a non-invasive option before considering more invasive interventions. However, it is not suitable for everyone. Your physiotherapist will discuss relevant precautions and assess factors such as pregnancy, blood-clotting issues, certain medications, recent steroid injection near the treatment area, suspected rupture or other medical considerations. It is also important to seek urgent medical advice if you experience a sudden pop in the back of the ankle, immediate weakness when pushing off, marked bruising or an inability to rise onto your toes. These can be warning signs of an Achilles rupture. Why Choose Weaver Physio? Weaver Physiotherapy & Sports Injury Clinic combines clinical assessment with a practical understanding of sport, training and everyday activity. We are based in Northwich and regularly support patients travelling from Knutsford, Alderley Edge, Holmes Chapel, Middlewich and across Cheshire. Our approach is built around three principles: Accurate assessment We identify the likely driver of your Achilles pain rather than treating every heel problem the same way. Evidence-informed rehabilitation Shockwave therapy is used as one part of a clear, progressive plan designed to restore strength and confidence. A return to the life you enjoy Whether your goal is pain-free dog walks, a hiking holiday, club running or competitive sport, your programme is shaped around it. Book an Achilles Tendon Assessment Persistent Achilles pain does not have to dictate how active you can be. If you are looking for shockwave therapy for Achilles tendinitis in Knutsford, Weaver Physio can help you understand your options and build a tailored recovery plan. Contact Weaver Physiotherapy & Sports Injury Clinic to arrange an assessment: Book or contact Weaver Physio 01606 227 484 07795 908 027 110 Middlewich Road, Northwich, CW9 7DP Frequently Asked Questions Is shockwave therapy painful? Most people describe shockwave therapy as uncomfortable rather than painful. The feeling is similar to firm tapping against the skin, and the intensity can be adjusted throughout treatment. Mild soreness, redness or tenderness can occur afterwards and usually settles within a few days. How many sessions will I need? Many patients have a course of three to five sessions, usually one week apart. Your clinician will recommend an appropriate plan based on your symptoms, tendon presentation and response to treatment. Can I exercise after shockwave therapy? Light daily activity is usually encouraged, but your clinician may advise avoiding high-impact exercise—such as running, jumping or hard hill work—for a short period after treatment. You will be given clear guidance on what to continue, reduce and progress. Will shockwave therapy cure my Achilles pain? No treatment can guarantee a cure. Shockwave therapy may help reduce pain and support recovery in suitable cases, but lasting improvement usually depends on combining treatment with a progressive loading programme, sensible activity management and a gradual return to sport.
September 16, 2026
A Complete Guide to Recovery and Better Running
September 16, 2026
A Non-Invasive Approach to Chronic Tendon Pain
September 15, 2026
Expert Physiotherapy for Nerve Pain, Back Pain and Lasting Recovery
September 10, 2026
Expert Treatment for Recovery, Mobility & Performance
September 9, 2026
Expert Physiotherapy for Vertigo, Dizziness & Balance Problems
September 7, 2026
The Expert Runner’s MOT
Show More